
Revenue cycle management
Revenue cycle management where one team owns the outcome, not just a task
A claim gets denied. Your coder says the documentation supported it. Your biller says the code was wrong. Your front desk says the insurance was what the patient gave them. Everyone is doing their job, and the claim is still sitting there at ninety days.
House of RCM takes the whole cycle. Eligibility, coding, submission, posting, denials, AR follow-up, and patient balances under one team inside your existing EHR, at 3% of what we collect. There’s nobody to hand the problem to, which is the point.
3% of collectionsEvery stage, one teamNo long-term contract
Free revenue review
Four fields. HIPAA compliant, and never shared.
- 5+ years in business
- 25+ specialties
- All 50 states
- US-based team
- HIPAA compliant, BAA signed first
What practices get with House of RCM
The numbers behind our service, from claim submission to support.
Clean claims on submission
Increase in claims
Billing submitted
Fastest electronic claim turnaround
US-based support
HIPAA compliant
A review shows where your own revenue cycle stands today.
Every vendor owns a task. Nobody owns the result.
Most practices didn’t choose a fragmented revenue cycle. They assembled one, a piece at a time, as each problem came up. A coding service here, a credentialing vendor there, billing somewhere else, and the front desk covering whatever nobody was contracted for.
Each one does its part correctly. The revenue leaks in the gaps between them, and every gap looks like somebody else’s job, which is exactly why it stays there for years.
Coder never sees the denial
The rejection goes to billing. The coder who assigned the code never learns which payer refuses which pairing, so it repeats.
Biller can't fix the note
A medical necessity denial needs documentation nobody outside your practice can change, so it gets appealed and lost.
Credentialing isn't billing's problem
Claims go out for a provider whose enrollment isn’t active yet, and the denials look like a billing failure.
Front desk owns eligibility
The most consequential quality step in the cycle is handled between check-ins, by whoever is at the desk.
Nobody owns the number
Every vendor reports on their piece. No one reports on whether you actually collected more this quarter.
A review traces a sample of your denials back through the chain to where they actually started.
What is revenue cycle management?
Revenue cycle management is the end-to-end financial process of a medical practice, from the moment a patient is registered to the moment the final dollar on that encounter is collected. It covers eligibility verification, prior authorization, coding, charge capture, claim submission, payment posting, denial management, accounts receivable follow-up, patient billing, and the reporting that ties all of it together.
Medical billing is one component of that, not a synonym for it. Billing submits claims and collects on them. Revenue cycle management includes everything that determines whether a claim was collectable before it was ever submitted, and everything that happens after it’s paid at the wrong amount.
The practical difference is where responsibility sits. A billing vendor is accountable for claims. An RCM partner is accountable for what you collect, which includes the eligibility step that wasn’t done, the charge that never got captured, and the provider whose credentialing lapsed.
Want to know whether you need billing or full RCM? A review tells you which gaps you actually have.
Every stage of your revenue cycle, handled by one team
Each stage feeds the next. Problems caught early cost nothing. The same problem found at AR has already cost you the claim, the rework, and the time.
Registration and eligibility
Demographics captured accurately and coverage confirmed before the visit, because the cheapest denial is the one that never happens.
Prior authorization
Approvals secured before the date of service, with expiration tracked against the scheduled procedure.
Medical coding
ICD-10, CPT, and HCPCS checked against documentation by experienced coders, with queries sent back rather than coded around.
Charge capture and submission
Your schedule reconciled against entered charges daily, then claims scrubbed to payer rules before they go out.
Payment posting
ERA and EOB posted at line level and reconciled daily, with underpayments flagged rather than absorbed.
Denial management
Every denial categorized by reason, given the remedy that reason calls for, and traced to the step that produced it.
AR follow-up
Aging worked by dollar value against remaining filing time, not top to bottom or oldest first.
Patient billing
Statements on a set cycle, online payment, plans on larger balances, and a support line patients can actually reach.
Provider credentialing runs alongside the cycle rather than inside it, and is priced separately at $100 per payer application so practices that only need enrollment work aren’t paying for billing. Credentialing services
All eight stages are included at 3% of collections. There’s no per-stage pricing.
Your accounts, your data, your systems
We work inside your EHR and your practice management system. Your patient records, your claim history, your payer contracts, and your reporting stay yours, in software you control, under logins you own.
That matters most on the day you’d want to leave. A practice whose revenue cycle lives inside a vendor’s proprietary platform isn’t choosing whether to stay with that vendor. Switching means a migration, and the vendor knows it.
There’s no long-term contract here for the same reason. If the numbers aren’t better in six months, the exit should be a conversation, not a project.
What that means in practice
Nothing migrates to a platform we own. We work in your system, with access you grant and can revoke.
Your claim history, payer correspondence, and appeal records stay in your system, visible to your staff in real time rather than in a monthly report.
No long-term contract and no minimum term. We’d rather keep your account by performing than by making leaving expensive.
If you do leave, there’s nothing to extract. It was always in your system.
Currently locked into a vendor platform? Ask us what an exit would actually involve.
Reporting tied to what you collected, not what we did
Most RCM reporting measures activity: claims submitted, calls made, appeals filed. All of it can go up while your collections go down. The only number that settles the question is what landed in your account.
- Collections by payer, trended month over month
- Net collection rate against what was collectable
- Days in AR and AR by aging bucket
- Denial rate by reason category and by payer
- First-pass clean claim rate
- Charge capture against scheduled encounters
- What we changed this month, and what it moved
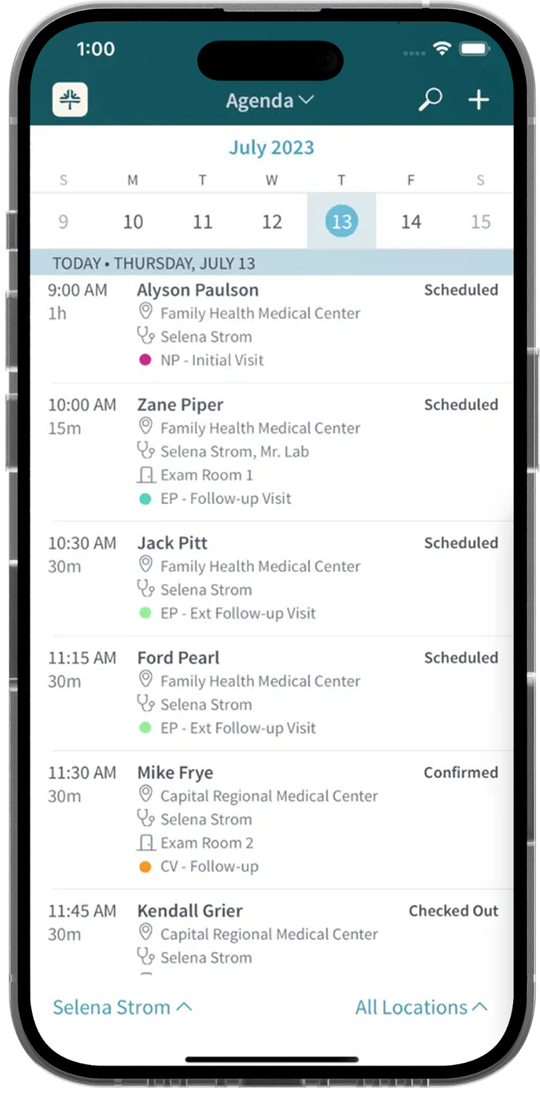
Ask to see a real monthly report before you commit to anything.
Revenue cycle management pricing: 3% of collections
One percentage covering all eight stages. Not 3% for billing plus a coding fee plus a statement charge plus a clearinghouse subscription. If we don’t collect, we don’t earn, which is the only arrangement where our incentive and yours point the same direction.
of monthly collections, all eight stages
- Eligibility verification and prior authorization
- Medical coding by experienced coders
- Charge capture, scrubbing, and submission
- Payment posting and reconciliation
- Denial management and appeals
- AR follow-up and underpayment recovery
- Patient billing, statements, and payment plans
- Monthly reporting and a dedicated account manager
No setup fee. No software fee. No per-claim charge. No long-term contract.
Credentialing billed separately at $100 per payer application.
What your current setup costs in total
Add up everything you currently pay across the cycle, then compare it to one rate.
Estimate only, from figures you enter. Include only the staff time actually spent on revenue cycle tasks.
Billing only, if that's all you need
Not every practice needs the full cycle. If your coding and front-end work are solid and you only want claims and AR handled, that’s the billing service rather than this one, at the same 3%. We’ll tell you which one fits on the call instead of selling the larger scope by default. Medical billing services
Send your collections and current vendor costs and we’ll give you the comparison before any work starts.
In-house and multi-vendor versus one team
The comparison most practices never make honestly is the total: not the billing rate, but every cost across the cycle plus the revenue that leaks between the people handling it.
| Metric | In-house or multi-vendor | House of RCM |
|---|---|---|
| Total cost | Billing rate plus software plus staff plus per-service fees | 3% of collections, all inclusive |
| Who owns the outcome | Nobody. Each party owns a task | One team, one account manager |
| Denial feedback to coding | Rarely happens across vendors | Same team sees the denial and the chart |
| Coverage during absence | That function stops | Team coverage, no gap |
| Reporting | One report per vendor, on their own piece | One report, on what you collected |
| Where your data lives | Split across vendor platforms | Your system, your logins |
| Scaling with volume | Hire, train, or renegotiate | Immediate |
If your current setup is working and you can prove it with a collection rate, keep it. The case for consolidating is strongest when nobody can tell you why last quarter was down.
Tell us what your current setup looks like and we’ll say plainly whether consolidating helps.
How the transition actually works
Switching an entire revenue cycle sounds like a project. Here’s what it involves, and what your staff has to do during it, which after access is close to nothing.
Step 1 · week 1
Free revenue review
We pull your denial rate, AR aging, clean claim rate, charge capture, and payer mix, and show you where revenue is leaking before you commit.
Step 2 · setup
Access and setup
Role-based HIPAA-compliant access inside your EHR, fee schedules loaded, provider enrollment status verified for every payer you bill.
Step 3 · transition
Parallel running
We run alongside your current process rather than replacing it overnight. No claim gaps, no missed filing deadlines, no dip in cash flow.
Step 4 · ongoing
Full cycle
All eight stages under your assigned team, with one account manager who knows your payer mix and answers directly.
Step 5 · monthly
Review against the baseline
The same numbers from week one, measured the same way, so the change is visible rather than asserted.
Once your account is live, billing is submitted within 24 hours.
Step one costs nothing and you keep the findings either way.
Specialty-matched across every stage
A generalist can run a revenue cycle. What they can’t do is know which modifier your payer expects, which documentation gap triggers your most common denial, or which of your codes goes unbilled most often.
Primary care
E/M leveling and chronic care codes, which are among the most consistently underbilled services in medicine.
Behavioral health
Session limits, authorization renewals mid-course, and time-based codes paired with medication management.
Therapy services
Timed code unit math and authorized visit limits, where exceeding the approved count is the most common loss.
Surgical specialties
Global periods, multiple procedure sequencing, and assistant roles that need the operative note to be billable.
OB/GYN
Global obstetric packages, antepartum counts, and services billed outside the package.
Pain management
Authorization-heavy, procedure-heavy, and frequently disputed on medical necessity.
Orthopedics
Laterality, implant coding, and fracture care global rules, with workers comp often a meaningful share.
Urgent care
Volume and same-day charge capture, where an encounter not coded today often never gets coded.
We cover more than 25 specialties. Tell us yours and we’ll name its usual failure points.
Built for your practice size
Solo providers
One unworked denial hits proportionally harder here than anywhere. Percentage pricing means you never pay for capacity you don’t use.
Group practices
Payments posted against the correct provider NPI rather than aggregated, so compensation and productivity data stays accurate.
Multi-specialty clinics
Specialty-matched staff per service line rather than one generalist covering orthopedics and behavioral health the same week.
Telehealth and multi-state
Place-of-service rules, state telehealth policies, and payer enrollment tracked per provider per state.
The rate is the same at any size: 3% of what we collect.
We work inside your system. Your staff never learns new software.
We operate inside your existing EHR and practice management system from day one, with role-based HIPAA-compliant access configured during onboarding. Your team doesn’t migrate data, export records, or change a single workflow.





List only platforms your team has hands-on experience in, with descriptive alt text on each logo.
Using something not listed? Bring it to the first call. We work with your clearinghouse too.
US-based team, all 50 states, BAA signed first
Every claim on your account is worked by someone in the United States, and when you call you reach a person who knows your payer mix rather than a general queue. Payer rules change at the state line, and Medicaid behaves differently in every one.
BAA signed first
Executed before access is granted, not after onboarding starts.
Role-based access
Each team member reaches only the records their function requires. Access is logged and reviewed.
Secure safeguards
Physical, electronic, and procedural safeguards protect your data, and only authorized staff can reach it.
Ongoing monitoring
We regularly review and improve our security practices, and we never sell or rent your information.
Want to see the BAA before anything starts? Ask and we’ll send it.
Client results
What practices say after consolidating their revenue cycle
Reviews from practices whose full revenue cycle House of RCM runs. Each one can be opened on the platform it came from.
★★★★★
“One of the best decisions I have made to improve the functioning of my business was to outsource my medical billing. House Of RCM Billers take the challenging and intricate task of billing off of my plate so that my team can do what it does best! I am so grateful for their services. As a client for over ten years, I can attest to their dedication, hard work, and attention to detail.”
Client for 10+ years
★★★★★
“I love everyone at House Of RCM. I’ve been using them for 7 years at this point for 2 of my businesses. Nothing but class, professionalism and great service. They address all of our need and go above and beyond to keep us happy. I’d recommend them to everyone and anyone.”
Client for 7 years, 2 businesses
Want to speak with a practice in your specialty before deciding? We’ll connect you.
FAQ
Questions practices ask about RCM
Question not covered here? A specialist will answer it on a call, no sales script.
What is revenue cycle management?
It’s the end-to-end financial process of a practice, from patient registration to final payment. It covers eligibility, prior authorization, coding, charge capture, claim submission, payment posting, denial management, AR follow-up, patient billing, and the reporting that connects them.
What's the difference between medical billing and revenue cycle management?
Billing submits claims and collects on them. RCM includes everything that determines whether a claim was collectable before submission, and everything that happens after it’s paid at the wrong amount. Billing is one component, not a synonym.
How much does revenue cycle management cost?
House of RCM charges 3% of monthly collections for all eight stages. No setup fee, no software fee, no per-claim charge, and no long-term contract. Credentialing is billed separately at $100 per payer application.
Do I need full RCM or just billing?
Depends where your gaps are. If your front-end work and coding are solid and you only need claims and AR handled, that’s the billing service at the same rate. We’ll tell you which fits on the call rather than selling the larger scope by default.
Do I have to change my EHR?
No. We work inside the system you already use, with access configured during onboarding. Your staff keeps its workflow and nothing migrates to a platform we own.
Who owns the data?
You do, and it stays in your system. That matters most on the day you’d want to leave: a practice whose revenue cycle lives in a vendor’s platform isn’t really choosing whether to stay.
Is there a long-term contract?
No, and no minimum term. If the numbers aren’t better in six months, leaving should be a conversation rather than a project.
How long does the transition take?
Once your account is live, billing is submitted within 24 hours. We run parallel with your current process during the transition, so there’s no gap in claim submission and no missed filing deadlines.
What reporting will I get?
Collections by payer, net collection rate, days in AR by bucket, denial rate by reason and payer, clean claim rate, charge capture rate, and what we changed this month. Reporting tied to what you collected rather than what we did.
Will the same team handle coding and denials?
Yes, and that’s the main argument for consolidating. A coder who never sees the denial never learns which payer refuses which pairing, which is why the same denial keeps arriving in a fragmented setup.
Does it work for a solo practice?
Yes, and solo practices often benefit most. One unworked denial hits proportionally harder without other billers covering for each other, and percentage pricing means you pay on what gets collected.
Is outsourced RCM HIPAA compliant?
Yes, when the vendor executes a Business Associate Agreement and restricts access properly. We sign a BAA before touching any patient data, limit access by function, and transmit everything over encrypted channels with audit logging.
Find out where your revenue cycle is leaking
A review measures the six numbers on this page for your practice, traces a sample of denials back to the stage that caused them, and shows you which gaps between your current vendors are costing the most. You keep the findings whether or not you work with us.
Bring your AR aging report, your last three months of denial data, and a list of who currently handles what. That’s usually enough to find the gaps in the first conversation.
3% of collectionsNo long-term contractHIPAA compliant
Request your free revenue review
HIPAA compliant. Your information is never shared.